
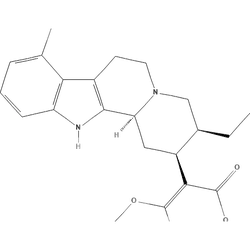
Mitragynine Stats & Data
COC=C(C(=O)OC)C1CC2N(CCc3c2nc2cccc(OC)c23)CC1CCLELBFTMXCIIKKX-MYLQJJOTSA-NPharmacology
DrugBankMechanism of Action
... Mitragynine (MIT), a mu-opioid agonist with antinociceptive and antitussive properties...
Metabolism
Mitragyna speciosa (Kratom) is ... a drug of abuse. When monitoring its abuse in urine, several alkaloids and their metabolites must be considered. In former studies, mitragynine (MG), its diastereomer speciogynine (SG), and paynantheine and their metabolites could be identified in rat and human urine using /Liquid Chromatography - Tandem Mass Spectometry/ (LC-MS(n)). In Kratom users' urines, besides MG and SG, further isomeric compounds were detected. To elucidate whether the MG and SG diastere
Measured Affinities
Guide to PHARMACOLOGYMeasured binding and functional data for mitragynine, curated by the IUPHAR/BPS Guide to PHARMACOLOGY. Each row cites the paper it came from. Lower concentrations mean tighter binding — a value in the sub-nanomolar range indicates a very potent interaction.
| Target | Action | Measure | Value | Concentration | Species | Source |
|---|---|---|---|---|---|---|
| μ receptor OPRM1 | Agonist | pEC50 | 9.3 | 0.501 nM | Human | PMID 34505767 |
| μ receptor Oprm1 | Agonist | pEC50 | 6.69 | 204.17 nM | Mouse | PMID 27556704 |
Reading this. pKi, pEC50 and pIC50 are negative log molar values, so a higher number means a tighter interaction; the concentration column converts them for you. Values from non-human species are laboratory measurements and do not translate directly to human effect. Receptor affinity is not a dose — it describes what a molecule binds, not how much of it is safe to take.
Receptor data from the IUPHAR/BPS Guide to PHARMACOLOGY (v2026.2), licensed CC BY-SA 4.0. Matched to this substance by InChIKey.
Effect Profile
CuratedModerate euphoria and focus with low stimulation
Moderate euphoria and sedation with moderate itching/nausea, mild pain relief
Tolerance & Pharmacokinetics
drugs.wikiNo tolerance chart. Our decay curves for opioids were estimates, and a curve can make tolerance look longer-lasting than it is, which is the dangerous direction.
Opioid tolerance drops fast when you stop, and even a few days off can be enough, so a dose that used to be normal can now stop your breathing. Overdose deaths rise sharply after prison, detox or leaving treatment, and tolerance also falls during a hospital stay. After any break, start with a much smaller amount, try a test dose first, don't use alone, and keep naloxone within reach. Alcohol, benzodiazepines, gabapentinoids and other sedatives make an opioid overdose much more likely.
Sources: FRANK: heroin · National Harm Reduction Coalition · WHO: opioid overdose · Merrall et al. 2010 · Binswanger et al. 2007 · Strang et al. 2003 · FDA 2019: gabapentinoids and breathing
Cross-Tolerances
Experience Report Analysis
ErowidDemographics
Gender Distribution
Too few reports for a chart: gender is known from 1 report, and a split is drawn only from 20 reports or more. Counts are shown instead. Why 20?
- Female 1 of 1
Reports Over Time
Harm Reduction
drugs.wikiKratom’s main alkaloids are mitragynine and, at much lower natural abundance, 7‑hydroxymitragynine (7‑OH). Oral mitragynine is hepatically oxidized (primarily via CYP3A isoforms) to 7‑OH, which mediates much of its MOR‑agonist analgesia; CYP3A inhibition can reduce both analgesia and mitragynine‑linked respiratory effects in animals, indicating route- and enzyme‑dependent effects. Treat kratom like an opioid for safety: combining with alcohol, benzodiazepines, other opioids, or GHB/GBL substantially increases overdose risks including respiratory compromise and aspiration, even if mitragynine shows biased agonism relative to classical opioids. Leaf potency is highly variable (mitragynine commonly 12–21 mg/g; some resins 35.6–62.6 mg/g), so dose titration is essential; avoid rapid re‑dosing because nausea and delayed peaks are common. Be wary of ‘enhanced’ or ‘fortified’ products: ‘Krypton’ products in Europe were adulterated with O‑desmethyltramadol and associated with deaths. Rare but documented kratom‑associated cholestatic liver injury exists; discontinue and seek care if pruritus, dark urine, jaundice, or severe abdominal pain occur. Pregnancy and lactation: neonatal opioid withdrawal has been reported with maternal kratom use; breastfeeding is discouraged due to unknown infant exposure to multiple CNS‑active alkaloids. Because mitragynine can inhibit CYP2D6/3A in vitro, co‑medications metabolized by these pathways (e.g., many antidepressants, antipsychotics, beta‑blockers, opioids) may have altered levels; avoid intentional potentiation with strong CYP3A inhibitors (e.g., grapefruit, certain azoles/macrolides) and monitor for adverse effects. High‑dose, chronic use can cause constipation, sweating, dizziness, and tolerance; maintain hydration, fiber intake, and consider periodic ‘off‑days’ to reduce escalation. Do not drive or operate machinery while sedated.
References
Cited references
- EUDA Kratom drug profile (chemistry, pharmacology, potency, adulterants, dependence)
- NCBI Bookshelf: StatPearls — Kratom (mechanism, metabolites, half‑life, biased agonism)
- NCBI PMC — Translating Kratom‑Drug Interactions: From Bedside to Bench and Back (CYP inhibition and DDI modeling)
- NCBI PMC — Exploration of cytochrome P450 inhibition mediated drug‑drug interaction potential of kratom alkaloids
- TripSit Drug Combinations (opioids + alcohol/benzos/GHB: high risk)
- NCBI Bookshelf: LactMed — Kratom (bioavailability, half‑life, neonatal withdrawal; breastfeeding advice)