
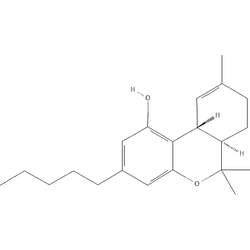
THC Stats & Data
CYQFCXCEBYINGO-IAGOWNOFSA-NPharmacology
DrugBankDescription
Dronabinol (marketed as Marinol) is a synthetic form of delta-9-tetrahydrocannabinol (Δ⁹-THC), the primary psychoactive component of cannabis (marijuana). THC demonstrates its effects through weak partial agonist activity at Cannabinoid-1 (CB1R) and Cannabinoid-2 (CB2R) receptors, which results in the well-known effects of smoking cannabis such as increased appetite, reduced pain, and changes in emotional and cognitive processes. Due to its evidence as an appetite stimulant and an anti-nauseant, Dronabinol is approved for use in anorexia associated with weight loss in patients with AIDS and for the treatment of nausea and vomiting associated with cancer chemotherapy in patients who have failed to respond adequately to conventional antiemetic treatments . Tetrahydrocannabinol (THC) and cannabidiol (CBD) are the two most abundant cannabinoids found naturally in the resin of the marijuana plant, both of which are pharmacologically active due to their interaction with cannabinoid receptors that are found throughout the body . While both CBD and THC are used for medicinal purposes, they have different receptor activity, function, and physiological effects. If not provided in their activated form (such as through synthetic forms like Dronabinol or DB00486), THC and CBD are obtained through conversion from their precursors, tetrahydrocannabinolic acid-A (THCA-A) and cannabidiolic acid (CBDA), through decarboxylation reactions.
Mechanism of Action
Dronabinol is a synthetic form of delta-9-tetrahydrocannabinol (Δ⁹-THC), the primary psychoactive component of cannabis (marijuana). THC demonstrates its effects through weak partial agonist activity at Cannabinoid-1 (CB1R) and Cannabinoid-2 (CB2R) receptors, which results in the well-known effects of smoking cannabis such as increased appetite, reduced pain, and changes in emotional and cognitive processes.
Pharmacodynamics
Marinol may has complex effects on the central nervous system (CNS), including cannabinoid receptors. Dronabinol may inhibit endorphins in the emetic center, suppress prostaglandin synthesis, and/or inhibit medullary activity through an unspecified cortical action.
Metabolism
THC is primarily metabolized in the liver by microsomal hydroxylation and oxidation reactions catalyzed by Cytochrome P450 enzymes. 11-hydroxy-▵9-tetrahydrocannabinol (11-OH-THC) is the primary active metabolite, capable of producing psychological and behavioural effects, which is then metabolized into 11-nor-9-carboxy-▵ 9-tetrahydrocannabinol (THC-COOH), THC's primary inactive metabolite . Dronabinol and its principal active metabolite, 11-OH-delta-9-THC, are present in approximately equal concentrations in plasma. Concentrations of both parent drug and metabolite peak at approximately 0.5 to 4 hours after oral dosing and decline over several days .
Absorption
Dronabinol capsules are almost completely absorbed (90 to 95%) after single oral doses. Due to the combined effects of first pass hepatic metabolism and high lipid solubility, only 10 to 20% of the administered dose reaches the systemic circulation. After oral administration, dronabinol has an onset of action of approximately 0.5 to 1 hours and peak effect at 2 to 4 hours. Following BID dosing of 2.5mg of dronabinol, Cmax was found to be 1.32ng/mL with a median Tmax of 1.00 hr.
Indication
For the treatment of anorexia associated with weight loss in patients with AIDS, and nausea and vomiting associated with cancer chemotherapy in patients who have failed to respond adequately to conventional antiemetic treatments
Half-life
The elimination phase of dronabinol can be described using a two compartment model with an initial (alpha) half-life of about 4 hours and a terminal (beta) half-life of 25 to 36 hours.
Protein Binding
The plasma protein binding of dronabinol and its metabolites is approximately 97%.
Elimination
Dronabinol and its biotransformation products are excreted in both feces and urine. Because of its large volume of distribution, dronabinol and its metabolites may be excreted at low levels for prolonged periods of time. Following single dose administration, low levels of dronabinol metabolites have been detected for more than 5 weeks in the urine and feces.
Volume of Distribution
Dronabinol has a large apparent volume of distribution, approximately 10 L/kg, because of its lipid solubility.
Clearance
Values for clearance average about 0.2 L/kg-hr, but are highly variable due to the complexity of cannabinoid distribution.
Measured Affinities
Guide to PHARMACOLOGYMeasured binding and functional data for Δ9-tetrahydrocannabinol, curated by the IUPHAR/BPS Guide to PHARMACOLOGY. Each row cites the paper it came from. Lower concentrations mean tighter binding — a value in the sub-nanomolar range indicates a very potent interaction.
| Target | Action | Measure | Value | Concentration | Species | Source |
|---|---|---|---|---|---|---|
| GPR55 GPR55 | Agonist | pEC50 | 8.1 | 7.94 nM | Human | PMID 17876302 |
| GPR18 GPR18 | Full agonist | pEC50 | 6.02 | 954.99 nM | Human | — |
| glycine receptor α2 subunit GLRA2 | Potentiation | pEC50 | 6 | 1,000 nM | Human | — |
| glycine receptor α1 subunit GLRA1 | Potentiation | pEC50 | 5.5 | 3,162 nM | Human | — |
| glycine receptor α3 subunit GLRA3 | Potentiation | pEC50 | 5.3 | 5,012 nM | Human | — |
| TRPA1 TRPA1 | Agonist | pEC50 | 4.9 | 12,589 nM | Human | PMID 14712238 |
| TRPV2 Trpv2 | Activation | pEC50 | 4.85 | 14,125 nM | Rat | PMID 18550765 |
| CB1 receptor CNR1 | Partial agonist | pKi | — | — | Human | — |
| CB2 receptor CNR2 | Partial agonist | pKi | — | — | Human | — |
Reading this. pKi, pEC50 and pIC50 are negative log molar values, so a higher number means a tighter interaction; the concentration column converts them for you. Values from non-human species are laboratory measurements and do not translate directly to human effect. Receptor affinity is not a dose — it describes what a molecule binds, not how much of it is safe to take.
Receptor data from the IUPHAR/BPS Guide to PHARMACOLOGY (v2026.2), licensed CC BY-SA 4.0. Matched to this substance by InChIKey.
Despite its reputation for being a benign substance, it is important to be aware that cannabis use is associated with distinct risks. Acute adverse effects include anxiety, hyperemesis syndrome, impaired coordination and judgment, suicidal ideations/tendencies, and psychotic symptoms.
Carcinogenicity
Under the conditions of these 2-year gavage studies, there was no evidence of carcinogenic activity of 1-trans-delta9-tetrahydrocannabinol in male or female F344/N rats administered 12.5, 25, or 50 mg/kg. There was equivocal evidence of carcinogenic activity of THC in male and female B6C3F1 mice based on the increased incidences of thyroid gland follicular cell adenomas in 125 mg/kg groups.
Liver injury risk
Ambiguous (limited data)
Addiction & dependence
Cannabis is moderately habit-forming. Research has shown the overall dependence potential for cannabis to be less than that for caffeine, tobacco, alcohol, cocaine or heroin, but higher than that for psilocybin, mescaline, or LSD. Dependence on cannabis is more common amongst heavy users.
Tolerance & Pharmacokinetics
drugs.wikiTolerance Decay
Based on human imaging and clinical studies showing CB1 down‑regulation with daily use and reversal over days–weeks. Model is approximate and varies with dose, frequency, and route. Data quality: mixed clinical/anecdotal.
Cross-Tolerances
Experience Report Analysis
ErowidDemographics
Gender Distribution
Age Distribution
Reports Over Time
Effect Analysis
ErowidEffects aggregated from 1,313 experience reports (1,313 single-substance Erowid)
Effect Sentiment Distribution
Confidence Distribution
Each bar is the share of reports mentioning the effect; its whisker, and the band on the rows below, is the 95% interval: where the share could plausibly be with other reports of the same kind.
Positive Effects 11
Adverse Effects 11
Show 8 neutral or unclassified mentions
Also reported in combinations. In the 3,637 THC reports where another drug was taken too, 362 (10.0%) mention hospital, emergency services or an overdose, 87 (2.4%) a seizure and 151 (4.2%) psychosis. In the 1,313 single-substance reports: 11.0%, 2.5% and 4.5%. These are not in the figures above: they cannot be put down to THC alone, and a mention is not always something that happened to the writer.
Dosage Distribution
Dose distribution from experience reports, one dose per report (the first listed). Doses above Q3 + 3×IQR, far above what people typically take, are left out of the median and range and listed under each route: most are real heavy doses or overdoses, not mistakes.
Smoked (cannabis, by weight)
Weight of cannabis as reported (flower, hash, edibles or extracts), not of THC, so it cannot be read against the THC dose ladder.
7 reports gave a dose above the typical range (5–10 g), so they are not in the figures above. Listing a dose here does not mean it is safe.
Oral (cannabis, by weight)
Weight of cannabis as reported (flower, hash, edibles or extracts), not of THC, so it cannot be read against the THC dose ladder.
1 report gave a dose above the typical range (23 g), so it is not in the figures above. Listing a dose here does not mean it is safe.
Show the report
Oral
1 report gave a dose above the typical range (80 mg), so it is not in the figures above. Listing a dose here does not mean it is safe.
Show the report
Real-World Dose Distribution
ErowidFrom 24 of 28 recorded dose entries: those that state a weight (mg, g or µg), in routes with at least five of them. Values above Q3 + 3×IQR, far above what people typically take, are left out; they can include real heavy doses and overdoses, not only mistakes.
Oral (n=23)
Common Combinations
Most co-occurring substances, as a share of all 4,950 reports filed under THC; whiskers are 95% intervals
Form / Preparation
Most common forms and preparations, as a share of the 2,755 reports that give one; whiskers are 95% intervals
Body-Weight Dosing
Dose per kg of body weight, one dose per report (the first listed), from reports giving a weight of 30–250 kg. Doses above Q3 + 3×IQR, far above what people typically take, are left out of the median and range and listed under each route.
1 report gave a dose above the typical range (0.735 mg/kg), so it is not in the figures above. Listing a dose here does not mean it is safe.
Show the report
Redose Patterns
Redosing behavior across 3695 reports
Harm Reduction
drugs.wikiHarm‑reduction additions and clarifications:
• “Start low, go slow,” especially with edibles: Oral THC has low/variable bioavailability and first‑pass conversion to 11‑hydroxy‑THC, which is more psychoactive and longer‑acting. Wait at least 2 hours before considering redosing to avoid delayed over‑intoxication. High‑fat meals can significantly increase oral THC exposure.
• Driving: Simulator and epidemiologic data indicate meaningful impairment for several hours after use, often beyond users’ self‑perception. Avoid driving or operating hazardous machinery for a minimum of 4–6 hours after inhalation and longer after higher oral doses; co‑use with alcohol markedly magnifies crash risk. THC can remain detectable long after impairment has resolved, especially in frequent users.
• Inhaled vapes: Avoid illicit/counterfeit THC cartridges; vitamin E acetate and other diluents were strongly linked to EVALI cases in 2019. Prefer regulated, tested products if vaping at all.
• Cannabinoid Hyperemesis Syndrome (CHS): Chronic, heavy use can cause cyclic vomiting relieved by hot showers; topical capsaicin may help acutely, but complete cessation is the definitive treatment.
• Cardiovascular and orthostatic effects: THC can cause tachycardia and vasodilation with orthostatic hypotension; people with significant cardiovascular disease should avoid or minimize THC.
• Mental health: Higher‑THC exposure, early onset, and heavy/frequent use are associated with increased risk of anxiety symptoms and psychotic‑like experiences; avoid if you have a personal or strong family history of psychosis, and prefer lower‑THC/higher‑CBD products if using.
• Adolescents/young adults: Because brains are still developing, initiate use later if at all; frequent adolescent use is linked to worse mental‑health and cognitive outcomes.
• Pregnancy and lactation: Avoid cannabis/CBD during pregnancy and while breastfeeding. THC crosses the placenta and is excreted into breast milk for days to weeks; potential neurodevelopmental risks are uncertain but concerning.
• Storage and pediatric safety: Edibles are a common source of accidental pediatric intoxication; store products in child‑resistant containers, locked and out of sight.
• Product variability: Non‑prescription CBD products and some cannabis edibles can be mislabeled for potency and purity; use lab‑tested, regulated sources when possible.
• Tolerance: With frequent use, CB1 down‑regulation produces tolerance to many subjective effects; tolerance reverses over days to weeks of abstinence, which also reduces withdrawal symptoms (sleep disturbance, irritability, appetite change).
• Genetics/phenoconversion: CYP2C9 poor metabolizers, or those taking CYP2C9 inhibitors, may experience stronger/longer effects from oral THC; start with lower doses.
References
Cited references
- DrugBank: Δ9‑Tetrahydrocannabinol
- NCBI PDQ: Cannabis and Cannabinoids—Pharmacology & Clinical
- NCBI Bookshelf: Cannabis—Effects of consumption on health
- StatPearls: Tetrahydrocannabinol (THC)
- StatPearls: Cannabinoid Toxicity
- StatPearls: Cannabinoid Hyperemesis Syndrome
- StatPearls: Cannabidiol (CBD) in Clinical Care
- NCBI Bookshelf (Medical Genetics Summaries): Dronabinol Therapy & CYP2C9
- NCBI Bookshelf: Clobazam—StatPearls
- NCBI Bookshelf: Clobazam Therapy and CYP2C19 Genotype
- NCBI Bookshelf: Review—Medical cannabis with other meds (safety/guidelines)
- DrugBank: Cannabidiol (CBD)
- EUDA: Cannabis and driving (policy brief)
- EUDA: Mini‑guide—Cannabis, public health messaging
- NCBI Bookshelf: MotherToBaby—Marijuana (Cannabis)
- LactMed: Dronabinol (THC)
- NCBI Bookshelf: Vaping‑Associated Lung Injury (EVALI)—StatPearls
- TripSit: Drug combination chart (cannabis)